This website uses cookies

We use cookies to enhance your experience and support COUNTER Metrics for transparent reporting of readership statistics. Cookie data is not sold to third parties or used for marketing purposes.

Skip to main content
null
NAPGO
  • Menu
  • Articles
    • Case Report
    • Conference Abstracts
    • Conference Bulletin
    • Expert Reviews
    • Original Research
    • Systemic Reviews
    • All
  • For Authors
  • Editorial Board
  • About
  • Issues
  • search
  • X (formerly Twitter) (opens in a new tab)
  • RSS feed (opens a modal with a link to feed)

RSS Feed

Enter the URL below into your favorite RSS reader.

http://localhost:41042/feed
ISSN 2769-5336
Case Report
Vol. 3, Issue 2, 2024May 05, 2024 EDT

Contained Uterine Rupture Managed Conservatively after Vaginal Delivery

Eric Schmitt, Thomas Choi, Jose Roble, Johmark Farlett, Abigail Schmolze,
uterine ruptureconservative managementhysterectomyprimary repairhematomabroad ligament hematoma
Copyright Logoccby-4.0 • https://doi.org/10.54053/001c.94680
Photo by engin akyurt on Unsplash

Articles in Vol. 3, Issue 2, 2024

Vol. 3, Issue 2, 2024
  • Wellness and diversity, equity, and inclusion support across residencies in core specialties - a national cross-sectional study
    Maggie WongLena FaiselDani ZoorobMalik MaysDanielle DeverJames Van Hook
  • Virtual schooling during the covid pandemic: the effect on high school retention for adolescent mothers
    Beatrice SoderholmJara CrawfordTracey WilkinsonDavid Haas
  • Vaginal cuff dehiscence with small bowel prolapse 10 years after vaginal hysterectomy
    Brandon MorehartDennis SchumacherDennis Lutz
  • Utilization of enhanced recovery after surgery (eras) protocol in gynecologic surgery
    Rachel HartmanSanela AndelijaNatalie HurlockJames BaronStephen ZweibachBradley SipeTiffany TonismaeMiriah Denbo
  • Uterine rupture secondary to pyomyoma leading to intraabdominal abscesses following an uncomplicated vaginal delivery
    Olga Colón-MercadoRachel HartmanJames BaronStephen ZweibachBradley SipeTiffany TonismaeLauren Davis
  • Uterine didelphys with transverse vaginal septum: a case report and review of the literature
    E. Baylee EdwardsKatherine GretteNicolette HollidayCandice Holliday
  • Twin-twin transfusion syndrome in the setting of covid-19 pneumonia: a case report
    Callie HamaiMegan WhiteTuhlei BreannaEric JohannesenElla SpeichingerAlbert Hsu
  • The impact of covid-19 vaccination on intrauterine fetal demise rates among pregnant women in the Metro-Detroit area
    Nicolina SmithMary CondonMariam AyyashGregory Goyert
  • The face of wellness, diversity, equity & inclusion: a national review of obstetrics & gynecology programs
    Malik MaysDani ZoorobLena FaiselDanielle DeverShahnaz VellaniJames Van Hook
  • The current state of medical informatics curricula in undergraduate medical education: a national survey
    Lauren LeibyAnita TamirisaDani ZoorobCatherine VanHook
  • Supplementing provider counseling with an educational video for scheduled induction of labor
    Kelsey PapeSierra CroweDavid Haas
  • Sorrows and the joys of tomorrow: analyzing maternal events during delivery and post-partum in the covid-19 pandemic through utilizing the epds
    Ala Addin Sid AhmedMaheen IrshadFederico Mariona
  • Second case of spontaneous left ureter rupture during normal spontaneous vaginal delivery
    Emily DeckerCollette LessardDennis Lutz
  • Sacral neuromodulation in a patient with pseudocholin-esterase deficiency
    Nadia MegahedPrapti SinghYaseen MalekiJames KirbyJulie Stewart
  • Religious and cultural diversity support across US based obstetrics and gynecology residency program
    Nabila AzeemDani ZoorobYasmin HasbiniJuliana ColvinAriel CohenJames Van Hook
  • Reduction in birth rates and preterm births following the emergence of COVID-19 pandemic in Michigan
    Mariam AyyashMegan McNittGregory Goyert,Madhurima KeerthyMonique Swain
  • Racial bias in cesarean decision making
    Sarah EdwardsQuetzal ClassCatherine FordTamika AlexanderJonah Fleisher
  • Race/ethnicity bias and its role in severe maternal morbidity: a clinical perspective
    Elliot LevineLeah DelfinadoCarlos Fernandez
  • Pregnancy outcome after placement of laminaria and subsequent second trimester removal
    Margaret MonroeTiffany TonismaeRaphael Guichard
  • Preferences and satisfaction of pregnant patients and ob nurses regarding monoclonal antibody infusions for the treatment of covid-19 pneumonia
    Katherine ChenDani ZoorobDavid HarperTracy BuderSamantha AchaeurJames Van Hook
  • Perinatal and maternal outcomes in singleton preterm births of african american versus caucasian women with hypertensive disorders
    Chinemelum OrizuJose PrietoTiffany Tonismae
  • Patient variables which lead to election of early vs. late post cesarean section discharge
    Benjamin KitkoMelissa VassasJames WilsonMichael Krew
  • Partner support has limited influence on clinical outcomes in pregnant patients with substance use disorder
    Neil PatelCynthia CockerhamLeon SuArnold StrombergBarbara ParillaJohn O'Brien
  • Optimal glucose testing for the detection and diagnosis of prediabetes and type ii diabetes mellitus in reproductive age women with polycystic ovarian syndrome
    Wenqi OuyangJaycee HoushRaquel IbarraKathleen GroeschTeresa WilsonPaula Diaz-SylvesterKristin DelfinoJ Ricardo Loret de Mola
  • Obstetrical and neonatal outcomes of pregnancies complicated by sarcoidosis
    Erin EganLaura DiGiovanniChristian AscoliNadera Sweiss
  • National chorioamnionitis trends: Geospatial analysis of vulnerable communities
    Joanne ChanNicholas PetermanBradley KapturRachel MannBrittany VillKristine Carpenter
  • Maternal and infant morbidity and mortality in extremely premature infants - a single centered study in detroit michigan between 23-26 weeks of gestation
    Mariam AyyashKrishna MajmundarGayathri VadlamudiDavid DaCostaGregory Goyert
  • Low-dose aspirin initiation rates in appropriate candidates at an academic residency program in the midwest
    Alexandra Mahdasian-MillerShachia JacksonDavid HaasCaroline Rouse
  • Impact of previous gynecologic care and gynecology service consults on abnormal uterine bleeding follow-up
    Khloe PastoreCaley PolkinghornNicolette CodispotiAnne TjadenLinda Yang
  • Identifying the palliative care needs of patients and families in gynecologic surgical oncology
    Klaudia KukulkaKarle WashingtonMary FaurotRachel AlexanderKevin CraigJean GoodmanErin Tuller
  • Hot yoga for pregnancy: a survey of hot yoga studio owners
    Elizabeth NikcevichViann Nguyen-FengBethany HansonShilpa Babbar
  • Homeopathic treatments of vulvovaginal candidiasis on youtube
    Breia ReedMaya BraggVeronica Mallett
  • Go nuts! Coconut oil as a patient-preferred alternative to commercial ultrasound gel
    Claire EdelmanCaroline RouseZiyi YangJoanne DaggyAnthony Shanks
  • Gastroschisis: To cut or not to cut?
    Mariam AboulelaAntonio Santos RocaAditi DeyPaul DanielsonTiffany Tonismae
  • Female dysorgasmia: an analysis of 19 patients who experience pain with orgasm
    Breton BarrierRaymond FosterMolly Greenwade
  • Factors that influence the choice for neonatal resuscitation in periviable deliveries
    Jessica YoungDiane CasiniTodd FosterTiffany TonismaePeter MarcusKelsey Montgomery
  • Evaluation of socio-economic and immune factors related to endometrial cancer
    Aneesh ChawlaStacy ParrTaylor BadgerEmily DirksKathleen GroeschTeresa WilsonPaula Diaz-SylvesterKristin DelfinoSarah NelsonJ. Ricardo Loret de MolaLaurent BrardAndrea Braundmeier-Fleming
  • Equitable time to treatment of severe hypertension among races at Cleveland Clinic Akron General
    Sarah DavisEstee GeorgeDavid BiatsRachelle AbdelnourCaroline MangiraNatalie Bowersox
  • Effect of pre-operative counseling on post-operative outcomes at the time of minor gynecologic surgery: a randomized control study
    Priscilla TingJason HoppeMichael Krew
  • Deciphering maternal ethnicity from state birth certificates: a perplexing quandary
    Jessica NelsonTiffany AzzarelloSteffen ChristensenThomas ArnoldDennis Lutz
  • Comparing delivery outcomes of concurrent use of mechanical dilation with low dose versus medium dose pitocin versus balloon catheter only
    Victor FeldbaumMaurice HordTiffany Tonismae
  • Colorectal adenocarcinoma presenting as a bowel obstruction in the second trimester of pregnancy
    Thomas ArnoldTracer OverlandDennis Lutz
  • Case of thoracoamniotic shunt placement for treatment of pleural effusion in the setting of congenital diaphragmatic hernia complicated by hydrops
    Antonio Santos RocaKelsey MontgomeryTiffany TonismaeDavid Kays
  • Buprenorphine induction using microdosing for the management of opioid use disorder in pregnancy
    Barbara Parillia
  • Atypical presentations of dicer1 syndrome in adults with juvenile granulosa cell tumor
    Callie HamaiSamantha SalmonArwa MohammadJean GoodmanMark Hunter
  • Atypical cerclage indication: a case report and review of the literature
    Rennan ZahariasWilliam PerezNicolette HollidayCandice Holliday
  • Association of gabapentin concentrations with opioid use after cesarean delivery
    David HaasRebecca SilvolaBobbie RayShelley DowdenAndrea MastersSara Quinney
  • Association between pregnant patients' characteristics and obtaining a biologic drug test
    Monika StoskuteAlexis BravermanDhanalakshmi Thiyagarajan
  • Arab american outcomes of pregnancies complicated by fetal growth restriction
    Nicolina SmithMichelle MillerRobyn GarciaGregory GoyertD'Angela Pitts
  • Application of the ovarian-adnexal radiological data-reporting system (o-rads) for ultrasound diagnosis and management of adnexal masses
    Carlos FernandezElliot LevineAbraham ShashouaIrma SodiniJacqueline LunaPena Maria de la Luz
  • A case series of four women with clear cell ovarian cancer, with unexpected atypical endometriosis as precursor lesions
    Abby LombardiEric JohannesenJane McElroyMark HunterErin TullerAlbert HsuJean Goodman
  • A Low Budget Perineal Repair Model
    Eric SchmittJose RobleJamie Humes
  • Conference Bulletin: Central Association of Obstetricians and Gynecologists - 2022
    North American Proceedings in Gynecology and Obstetrics
  • Donor Screening: Level of Sensitivity in Karyotype with GTG banding vs PGT-A with NGS
    Naveena DaramMeghan Ozcan
  • Contained Uterine Rupture Managed Conservatively after Vaginal Delivery
    Eric SchmittThomas ChoiJose RobleJohmark FarlettAbigail Schmolze
  • A systematic review of maternal exposures and the risk of autism spectrum disorders in their infants
    Shae N JansenKyle M BaughJames B AdamsChristina K FlynnDavid M Haas
  • Case Report: Dichorionic-Diamniotic Twin Pregnancy Complicated by a Migrational Anomaly Mimicking a Brain Neoplasm
    Eric SchmittPablo DelisSonia PintoVeronica RooksDonald Gloeb
NAPGO
Schmitt, Eric, Thomas Choi, Jose Roble, Johmark Farlett, and Abigail Schmolze. 2024. “Contained Uterine Rupture Managed Conservatively after Vaginal Delivery.” North American Proceedings in Gynecology & Obstetrics 3 (2). https://doi.org/10.54053/001c.94680.
Save article as...▾
Download all (5)
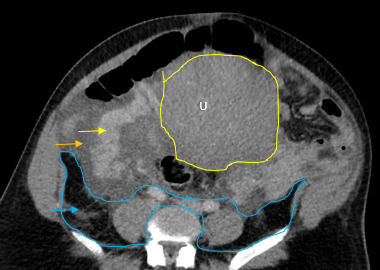
  • Figure 1. Axial CT with contrast of the upper uterine segment demonstrates dilated and elevated right ovarian vein (yellow arrow) within right sided intraperitoneal fluid (orange arrow), with asymmetric stranding on the right (blue arrow) of the retroperitoneal space (blue border)
    Download
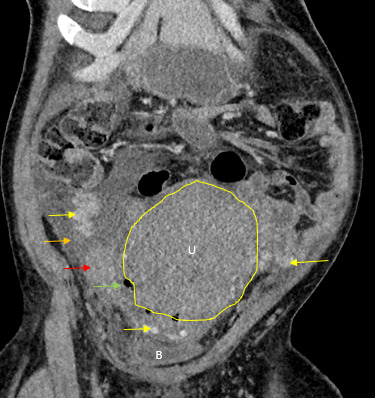
  • Figure 2. Coronal CT with contrast of the uterus demonstrates the periuterine vessels (yellow arrows) with right sided intraperitoneal fluid (orange arrow), hematoma of the broad ligament (red arrow) and peritoneal air accumulation (green arrow) outside the uterus (yellow border).
    Download
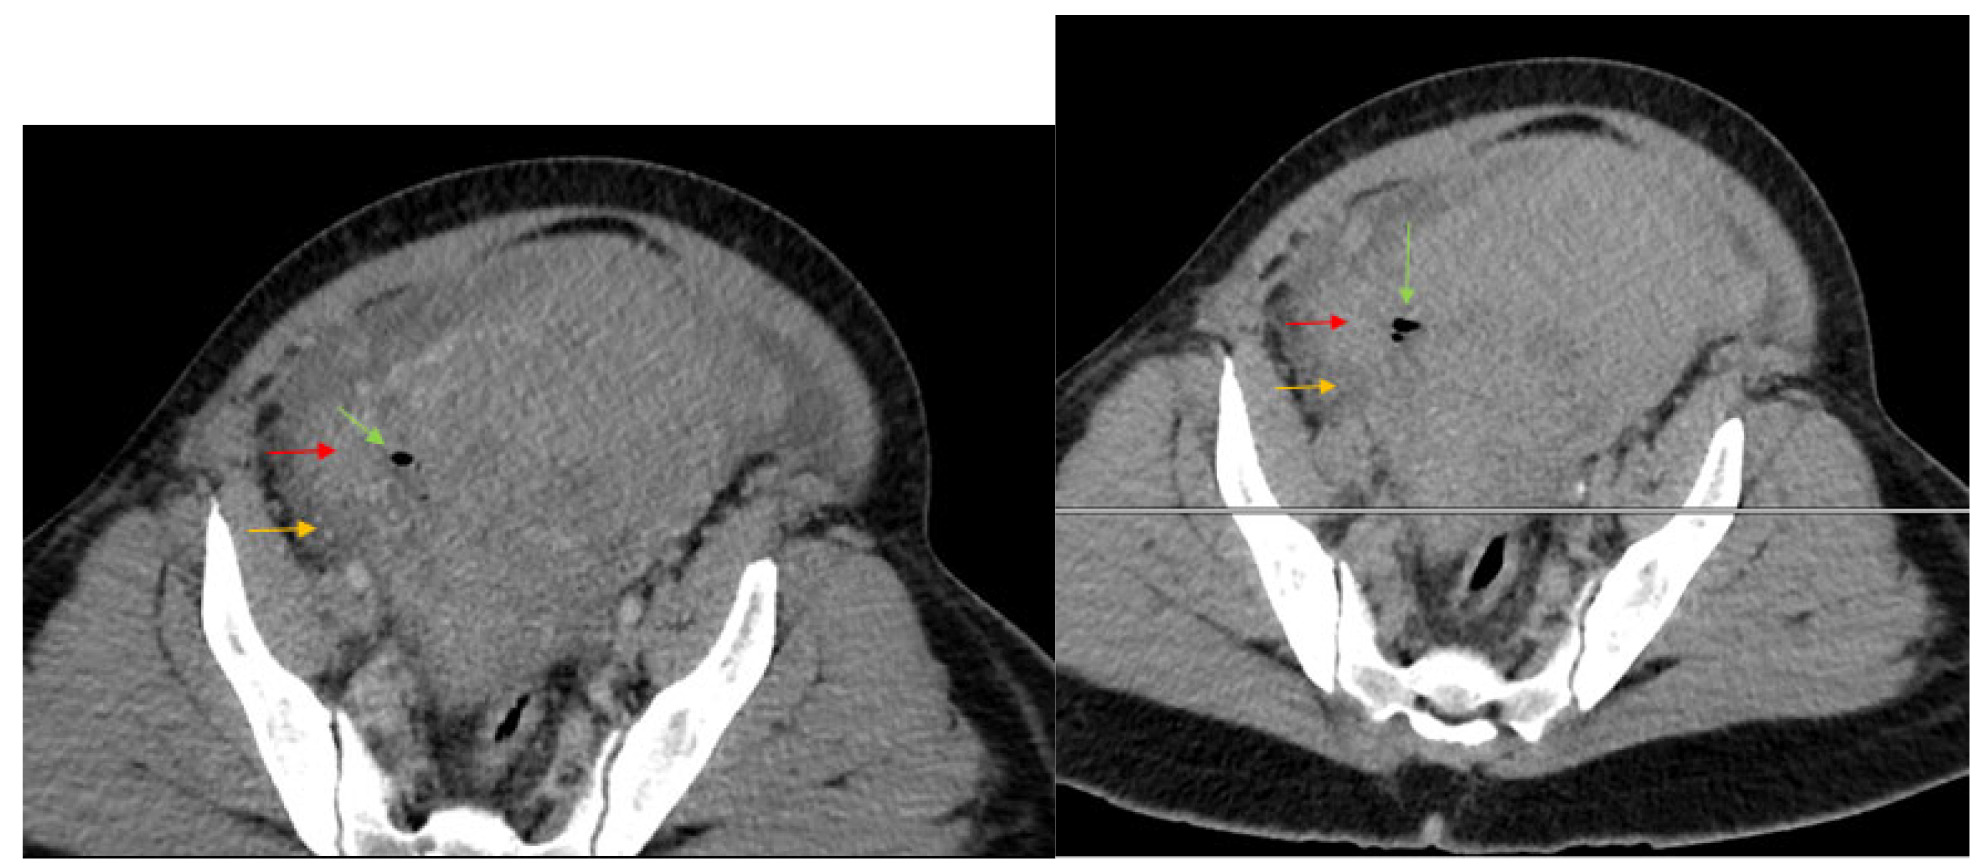
  • Figure 3-4. Axial lower uterine segment images in the portovenous phase (left) and delayed phase (right) demonstrate hypoattenuating endometrium appearing contiguous with the extra uterine fluid, through the myometrium, of the right lateral lower uterine segment.
    Download
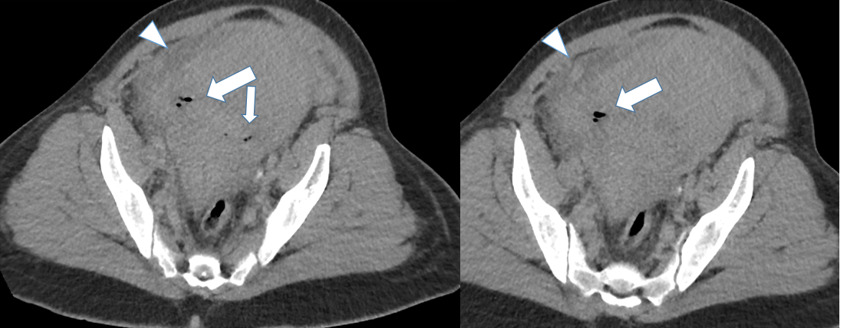
  • Figure 5-6. CT Abdomen notable for air present between the uterine myometrium and ovarian vasculature. Arrowhead noting contour abnormality along right parasagittal lower uterine segment thought to be the site of defect
    Download
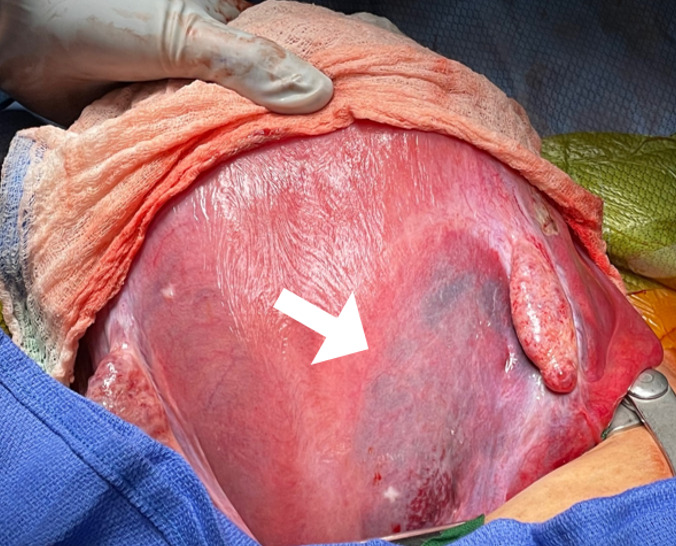
  • Figure 7. Intraoperative veiw of the left anterior inferior uterus. Solid arrow indicating 15 cm by 6 cm broad ligament hematoma overlying area of suspected defect
    Download

Error

Sorry, something went wrong. Please try again.

If this problem reoccurs, please contact Scholastica Support

Error message:

undefined

View more stats

Abstract

Background

Uterine rupture in an otherwise unscarred uterus is a rare event, with most sources describing it on the order of 1/5700 to 1/20,000 deliveries [1]. Risk factors include high multiparity, use of uterotonics, advanced maternal age, macrosomia, malpresentation, placental invasion, and prolonged labor [2-3]. Historically, management of this complication involves exploratory laparotomy with surgical repair or hysterectomy. Few reports have been published that describe conservative management in the setting of uterine rupture.

Objective(s)

To describe the conservative management of contained uterine rupture.

Study Design

Case report

Case Summary

A 39-year-old gravida 5, para 4 with history of pre-eclampsia was admitted for induction of labor at 40 weeks 0 days. Her intrapartum labor was complicated by pre-eclampsia with severe features. She had a vaginal delivery after 20 hours of induction without immediate complications. Following delivery, the patient complained of severe right lower quadrant pain, which was treated with escalating pain regimen, but continued to worsen. A CT scan was obtained, which revealed a right retroperitoneal hematoma with findings suspicious for uterine rupture. The patient was taken to the operating room for exploratory laparotomy with findings of a right-sided broad ligament hematoma measuring 15 cm by 6 cm, extending into the retroperitoneal space. The surgery ended without additional procedures since the patient was hemodynamically stable, and the hematoma was non-expanding. Postoperatively, she was started on a multimodal pain regimen, and eventually discharged on postoperative day 3 after pain improved.

Conclusion

We describe a contained uterine rupture noted in the immediate postpartum period after an uncomplicated vaginal delivery. Our patient had several risk factors for uterine rupture such as advanced maternal aged, high multiparity, and macrosomia. Surgical exploration noted a large non-expanding hematoma overlying the site of suspected uterine rupture, which was stable. In an otherwise hemodynamically stable patient with contained uterine rupture, conservative management is a reasonable option.

Introduction

Rupture on an unscarred uterus is a very rare event, with most sources describing it on the order of 1/5700 to 1/20,000 deliveries (“ACOG Practice Bulletin No. 205: Vaginal Birth After Cesarean Delivery” 2019). The risk factors for this complication are still being described, but typically include high multiparity, use of uterotonics, advanced maternal age, macrosomia, malpresentation, placental invasion, and prolonged labor (Al-Zirqi et al. 2015; Smith, Mertz, and Merrill 2008). Typically, the standard of care for management of uterine rupture is surgical management via open laparotomy to attempt to repair the rupture or to perform a hysterectomy (Peker et al. 2020). However conservative options, such as observing a patient that is otherwise clinically stable with a uterine defect is not unreasonable given recent clinical literature evaluating similar management options after large retroperitoneal or uterine hematomas noted after vaginal delivery (Rafi and Muppala 2008, 2009). In these case series, large non-expanding hematomas are often managed with observation instead of primary repair as the risk of opening this hematoma to access the original site of bleeding could result in more complications than allowing the bleeding to resolve on its own within a confined space.

We describe a case where this concept was used to guide conservative management of a uterine rupture noted after a vaginal delivery on an unscarred uterus. In our clinical scenario, this uterine rupture, which was identified on CT, caused the development of a large non-expanding hematoma which was contained by the serosa and broad ligament. This rupture and the associated hematoma were managed conservatively. This is this first case report of a confirmed uterine rupture managed in this way as previous case series have only discussed this technique for non-expanding retroperitoneal hematomas.

Case Summary

A 39-year-old gravida 5 para 4 female with a history of pre-eclampsia in a prior pregnancies was admitted for induction of labor at 40 weeks gestation. Her prenatal course was notable only for an uncomplicated COVID infection at 36 weeks gestation. Her induction of labor was complicated by pre-eclampsia with severe features in the setting of thrombocytopenia (96 x 109 platelets/μL) and elevated serum creatinine (1.18 mg/dL), and she was administered magnesium therapy for seizure prophylaxis. The patient had a protracted labor course but had an otherwise uncomplicated spontaneous vaginal delivery 20 hours after the start of her induction.

Immediately after delivery, the patient complained of severe right lower quadrant abdominal pain which was initially described as a 9/10 intense ache which worsened with movement. She was evaluated and noted to be hemodynamically stable with a mildly distended but extremely tender right abdomen. Pain management was attempted with acetaminophen, ketorolac, and eventually oxycodone, but these medications only provided mild temporary relief, and the patient quickly reported worsening pain shortly after each administration. Her vital signs were stable, and repeat abdominal exam was notable for guarding and a positive Rovsing and Psoas sign. A focused assessment with sonography in trauma (FAST) exam did not reveal evidence of peritoneal bleeding, but due to pain out of proportion with an otherwise uncomplicated vaginal delivery, computed tomography (CT) scan was obtained.

The initial impressions of the axial and coronal CT images revealed dilation of the right ovarian vein in addition to intraperitoneal fluid accumulation on the right side (Fig. 1-2). Portovenous and delayed phase images did not demonstrate contrast pooling or persistent hyperattenuation to suggest hyperacute hemorrhage (Fig. 3-4). Additionally, there was evidence of peritoneal air present between the uterine myometrium and ovarian vasculature most notable along the right aspect of the anterior inferior uterus. A contour abnormality along the right parasagittal lower uterine segment was also noted and interpreted as a uterine defect without signs of free intraperitoneal hemorrhage. In conjunction with her clinical picture, these radiologic findings raised our suspicion for a contained uterine rupture although there were no pathognomonic imaging findings to confirm an associated retroperitoneal hematoma. The patient was urgently taken to the operating room for an exploratory laparotomy to confirm the diagnosis and to manage surgically if indicated.
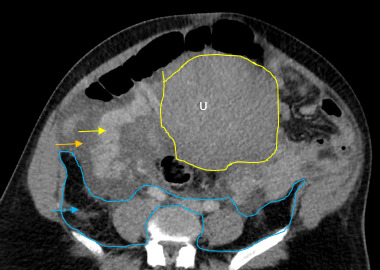
Figure 1
Figure 1.Axial CT with contrast of the upper uterine segment demonstrates dilated and elevated right ovarian vein (yellow arrow) within right sided intraperitoneal fluid (orange arrow), with asymmetric stranding on the right (blue arrow) of the retroperitoneal space (blue border)
Figure 2
Figure 2.Coronal CT with contrast of the uterus demonstrates the periuterine vessels (yellow arrows) with right sided intraperitoneal fluid (orange arrow), hematoma of the broad ligament (red arrow) and peritoneal air accumulation (green arrow) outside the uterus (yellow border).
Figure 3-4
Figure 3-4.Axial lower uterine segment images in the portovenous phase (left) and delayed phase (right) demonstrate hypoattenuating endometrium appearing contiguous with the extra uterine fluid, through the myometrium, of the right lateral lower uterine segment.

There was no evidence of hemoperitoneum upon abdominal entry. There was a minor 1 cm x 1 cm superficial serosal defect noted at the right cornua, which was hemostatic and secondary to manipulation of the uterus. Most notably, a large non-expanding right-sided broad ligament hematoma measuring 15 cm x 6 cm was noted extending into the retroperitoneal space over the site of suspected uterine rupture (Fig. 5-7). The patient remained hemodynamically stable intraoperatively, and following direct observation, the hematoma was noted to be non-expanding. The uterus was taken off tension, and the decision was made to close the patient without further intervention.

Figure 5-6
Figure 5-6.CT Abdomen notable for air present between the uterine myometrium and ovarian vasculature. Arrowhead noting contour abnormality along right parasagittal lower uterine segment thought to be the site of defect
Figure 7
Figure 7.Intraoperative veiw of the left anterior inferior uterus. Solid arrow indicating 15 cm by 6 cm broad ligament hematoma overlying area of suspected defect

Postoperatively, a multimodal pain control regimen was started, consisting of morphine, acetaminophen, and ibuprofen, which adequately controlled her pain. Patient was discharged on post-operative day 3 with minimal pain and a greatly improved abdominal exam. On post-operative day 7, the patient returned to the OBGYN Clinic for repeat evaluation, noting resolved pain and benign physical exam. She reported no other concerns throughout her postpartum period.

Discussion

Our case describes conservative management of a uterine rupture. In most cases of uterine rupture that occurs intrapartum, the diagnosis is made clinically with evidence from the physical exam in addition to changes in fetal heart rate tracing. However, in our case, her initial symptoms occurred immediately postpartum, and, imaging was necessary to make an informed decision for care. Therefore, expert consultation and collaboration with a multi-disciplinary team is critical to ensure proper and timely diagnosis.

Uterine rupture was highly suspected even prior to the exploratory laparotomy due to the presence of air between the uterine myometrium and the ovarian vessels. Figures 1-4 describe CT findings consistent with uterine rupture. This is the first case report of a uterine rupture being managed conservatively similarly to previously described management options for contained uterine hematomas.

While the CT raised our suspicion for uterine rupture preoperatively, it did not predict for the size and extent of the broad ligament hematoma that we observed intraoperatively. It was appropriate to perform an exploratory laparotomy as most uterine ruptures require surgical management. The decision to manage conservatively rested on the non-expanding nature of the hematoma, an intact broad ligament, and the patient’s hemodynamic stability. As these safety checks were passed, we decided to conservatively manage the defect and to avoid the more morbid hysterectomy as well as its potential complications.

In reviewing the current literature around uterine ruptures, several considerations are worth discussing. Our patient had several risk factors for uterine rupture including multiparity, use of uterotonics and cervical ripening agents, advanced maternal age, macrosomia, and obstructed labor. Peker et al. published a retrospective review in 2020 of 67 unscarred uterine ruptures which occurred at a Turkish tertiary care center over 12 years. This study suggested that in populations with one or more of these risk factors present, the incidence of uterine rupture after uncomplicated vaginal delivery may rise to a number closer to 1 out of 2770 women (Peker et al. 2020). It is notable that our patient had very similar but slightly lesser pain after her previous pregnancy that resolved spontaneously over 3-6 months and was not evaluated by postpartum imaging. It is possible that this uterine defect was present in the last pregnancy which may have caused a similar but perhaps smaller hematoma that resolved spontaneously. Puerperal and retroperitoneal hematomas are rare occurrences in the obstetrical literature, and only a handful of case reports have been published to describe management options (Rafi and Muppala 2008, 2009; Rafi and Khalil 2018; Kim et al. 2011; Alturki, Ponette, and Boucher 2018). In the past, these hematomas were thought to be exclusively iatrogenic and specifically noted after caesarean section. However, Rafi and colleagues describe a rare case of a massive hematoma following an uncomplicated spontaneous vaginal delivery that was managed conservatively. Our case is unique, however, as none of these described hematomas were confirmed to be secondary to a uterine defect.

While this is a unique management option in a very specific situation, it would not be appropriate if the patient had been hemodynamically unstable; surgical repair would have been warranted. Most ruptures occur at the isthmic region of the uterus, which is what we noted here as well. Fundal ruptures are typically more complicated and are associated with worse outcomes. While data on repeat pregnancies after unscarred uterine rupture is limited, the overall risk of recurrent rupture is somewhere between 22-100% based on a handful of case series (Gupta et al. 2016; Dow et al. 2009). Similarly, while there is no consensus on timing of repeated delivery, many physicians recommend a scheduled cesarean section at 36-37 weeks with an isthmic rupture and recommend choosing a date closer to 32-33 weeks for a higher risk fundal rupture (Landon and Grobman 2016). Patients, such as our own, should also be counseled appropriately regarding short interval pregnancy and future risk of rupture recurrence. In this case, our patient was not planning any future pregnancies.

In conclusion, rupture of an unscarred uterus is an extremely rare occurrence but can have catastrophic maternal and fetal outcomes. Once the diagnosis is made, the standard management of uterine rupture is emergent surgical management in the setting of hemodynamic instability and possible fetal distress during labor. Conservative management may be a reasonable option in select patients that are hemodynamically stable with a rupture that is contained and non-expanding. These ruptures likely have potential to self-resolve with supportive care, but proper counseling should be provided for future pregnancies and patients must be given clear recommendations on mode as well as timing of delivery. Our report, albeit specific to our patient, can be utilized as a guide for future providers in considering other alternatives to manage uterine rupture.

Submitted: December 14, 2023 EDT

Accepted: March 05, 2024 EDT

References

“ACOG Practice Bulletin No. 205: Vaginal Birth After Cesarean Delivery.” 2019. Obstetrics & Gynecology 133 (2): e110–27. https:/​/​doi.org/​10.1097/​aog.0000000000003078.
Google Scholar
Alturki, Faisal, Vincent Ponette, and Louis-Martin Boucher. 2018. “Spontaneous Retroperitoneal Hematomas Following Uncomplicated Vaginal Deliveries: A Case Report and Literature Review.” Journal of Obstetrics and Gynaecology Canada 40 (6): 712–15. https:/​/​doi.org/​10.1016/​j.jogc.2017.08.045.
Google Scholar
Al-Zirqi, I, B Stray-Pedersen, L Forsén, A-K Daltveit, and S Vangen. 2015. “Uterine Rupture: Trends over 40 Years.” BJOG: An International Journal of Obstetrics & Gynaecology 123 (5): 780–87. https:/​/​doi.org/​10.1111/​1471-0528.13394.
Google Scholar
Dow, Margaret, Joseph Wax, Michael Pinette, Jacquelyn Blackstone, and Angelina Cartin. 2009. “Third-Trimester Uterine Rupture without Previous Cesarean: A Case Series and Review of the Literature.” American Journal of Perinatology 26 (10): 739–44. https:/​/​doi.org/​10.1055/​s-0029-1223287.
Google Scholar
Gupta, Ridhima, Maruti Sinha, Pushpender Gupta, Rekha Rani, Ramanjeet Kaur, and Rahil Singh. 2016. “Uterine Rupture: A Seven Year Review at a Tertiary Care Hospital in New Delhi, India.” Indian Journal of Community Medicine 41 (1): 45. https:/​/​doi.org/​10.4103/​0970-0218.170966.
Google ScholarPubMed CentralPubMed
Kim, Y., J. Kim, H. Cho, and T. B. Song. 2011. “P18.01: A Case of Spontaneous Retroperitoneal Hematoma in Pregnant Woman.” Ultrasound in Obstetrics & Gynecology 38 (S1): 233–233. https:/​/​doi.org/​10.1002/​uog.9847.
Google Scholar
Landon, Mark B., and William A. Grobman. 2016. “What We Have Learned About Trial of Labor After Cesarean Delivery from the Maternal-Fetal Medicine Units Cesarean Registry.” Seminars in Perinatology 40 (5): 281–86. https:/​/​doi.org/​10.1053/​j.semperi.2016.03.003.
Google ScholarPubMed CentralPubMed
Peker, Nurullah, Edip Aydın, Mehmet Sıddık Evsen, Fatma Nur Hançer, Muhammet Hanifi Bademkıran, Serhat Ege, Bekir Kahveci, Talip Karaçor, and Talip Gül. 2020. “Unscarred Uterine Rupture and Subsequent Pregnancy Outcome — a Tertiary Centre Experience.” Ginekologia Polska 91 (2): 95–90. https:/​/​doi.org/​10.5603/​gp.a2020.0012.
Google Scholar
Rafi, Junaid, and Haroona Khalil. 2018. “Maternal Morbidity and Mortality Associated with Retroperitoneal Haematomas in Pregnancy.” JRSM Open 9 (1): 205427041774605. https:/​/​doi.org/​10.1177/​2054270417746059.
Google ScholarPubMed CentralPubMed
Rafi, Junaid, and Hari Muppala. 2008. “Conservative Management of Massive Puerperal Spontaneous Onset Retroperitoneal Psoas Muscle Haematoma Following Normal Vaginal Delivery.” Journal of Obstetrics and Gynaecology 28 (1): 105–6. https:/​/​doi.org/​10.1080/​01443610701846395.
Google Scholar
———. 2009. “Retroperitoneal Haematomas in Obstetrics: Literature Review.” Archives of Gynecology and Obstetrics 281 (3): 435–41. https:/​/​doi.org/​10.1007/​s00404-009-1282-y.
Google Scholar
Smith, Jennifer G., Heather L. Mertz, and David C. Merrill. 2008. “Identifying Risk Factors for Uterine Rupture.” Clinics in Perinatology 35 (1): 85–99. https:/​/​doi.org/​10.1016/​j.clp.2007.11.008.
Google Scholar

Attachments

Powered by Scholastica, the modern academic journal management system